Pages

Showing posts with label congenital heart defect. Show all posts

Saturday, April 7, 2012

"A Time I Had Courage"

I love William's second-grade teacher, Ms. Webb. She gets her students -- and especially my 8-year-old -- thinking about life ... in funny, silly and serious ways. One of her assignments recently was to have her students write about "A Time I Had Courage." 

William was only 27 months old the time he had to have the most courage ever, so he has little if any original memory of this time, but we have talked to him about it enough, he has seen photos of this time enough, and he has heard us tell his story to others enough, that he knows a lot about this particular time he had courage. 

I'm not going to tell his story this time, though. He has done that all on his own . With William's permission, here is his story about "A Time I Had Courage."


Monday, December 12, 2011

Don't Be Afraid to Ask for a Heart Screening

Today, I read another story about a high-school athlete who dropped dead during practice from an undiagnosed, undetected congenital heart defect. The 17-year-old was at lacrosse practice. The very sport my high-school-athlete son plays.

I am relieved to know now that my son Martin has a healthy heart. Earlier this year, I finally asked our pediatrician to screen him for congenital heart disease (CHD). I had let the question nag me since 2005, when my younger son William was diagnosed with Scimitar Syndrome. Martin was screened in March, after I read news stories about five student athletes who collapsed and died while playing their sport.

I'm so sad for Daniel Valenson's family. They had no way of knowing. The heart defect he had (anomalous left coronary artery from the pulmonary artery) is very rare -- affecting 1 in 50,000 to 1 in 300,000 live births -- and often, the first symptom or sign of trouble is sudden cardiac death.

While Daniel's particular heart defect is very rare, congenital heart defects are not rare. They are frighteningly common, and yet, our children are not routinely screened for them at birth or as a requirement to play organized sports, although there are efforts to change this. In Chicago, for example, privately funded screenings have saved the lives of area athletes.

Congenital heart defects strike an average of 1 in 100 babies. Heart defects are THE MOST COMMON of ALL birth defects. More common than the ones you hear so much about -- and many of which women are routinely screened for during pregnancy -- such as spina bifida, Down syndrome, cleft lip and palate, and abnormal extremities.

Congenital heart disease affects about 35,000 children each year in the United States. Of those, about 3,500 die before their first birthday. Nearly twice as many children die from CHDs in the United States each year as from all forms of childhood cancers combined.

Don't be afraid to ask your pediatrician or family physician for your newborn, infant, toddler, young child or your student athlete to be screened for congenital (or acquired) heart disease. 

While any physician may be able to identify a congenital heart defect, the most qualified and specially trained physicians in this area are those who are board-certified in pediatric cardiology. Certification matters!

Congenital heart defects can be found through:
Another startling fact about congenital heart disease: About 10 percent of all CHD cases that are evaluated in adult congenital heart clinics are first diagnosed in adulthood — that means there are adults walking around today who have undiagnosed congenital heart defects.
  
Screening does not require invasive testing. Diagnosis and treatment saves lives. Now more than ever, people with congenital heart disease are living longer, active, normal lives. 

Ask.


Wednesday, June 29, 2011

Happy Heart Day, William! Five Years!

Five years ago today, we gave our son over to the pediatric heart team with the UF Health Congenital Heart Center so they could fix his heart. Some days it feels like it was just yesterday, other days like it was a lifetime ago.

But one thing that never wavers or changes is our gratitude. Five years later, we are still so grateful to our pediatrician Dr. Dean Dalrymple and local pediatric radiologist Dr. Charles Williams, who finally diagnosed William at age 1, after he'd been so sick for a year. Grateful to Dr. Jay Fricker for taking care of William's heart until Shands hired a pediatric heart surgeon. Deeply grateful to that pediatric heart surgeon -- Dr. Mark Bleiweis -- for choosing Shands and for Shands choosing him. Because of these doctors, William is a happy, healthy, soon-to-be second grader who doesn't have a care in the world.

William, immediately after surgery to
repair his partial anomalous
pulmonary venous return, June 29, 2006.


William with big brother Martin, the day after surgery.
Uncomfortable, but loved listening to his bunny's heart.
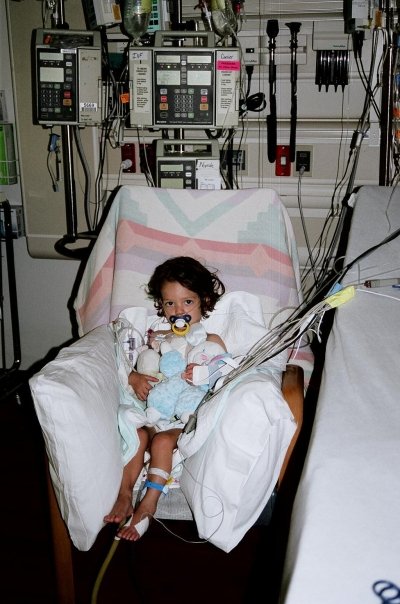
Sitting up in a chair the day after surgery.
Not a happy camper, but when his brother
asked, "Does it hurt?,"
William replied, "No, not much."
Hanging out in bed on Day 2, still feeling sore, still hooked
up to chest tubes that drained blood from his chest cavity.
Back in the chair again on Day 3. This
time he gives his Grandma a smile.
Day 4 and feeling good. Getting ready
to go home! Yes, surgery was on a
Thursday. We were HOME by the next
Monday! That's how William and
Dr. Bleiweis roll.
"Seriously, Dr. Bleiweis. I am SO ready to go home!"
Saying so long to his favorite PICU Nurse Josh Campbell.


Since surgery, we have yearly checkups. We have echos.
We have EKGs.
Sometimes, we have CT scans of our chest
and visit our surgeon so he can see how much |
we've grown and how awesome we're doing
(doctors love to see that with all their patients!)
We even go to Gainesville to walk in the AHA
Heart Walk with our pediatric cardiologist
and pediatric nurse. We love Shands and AHA!
But mostly, we simply revel in every day. Feeling blessed that everything is going so well, and that William is happy and healthy. If you'd like to read more about William's journey, go to www.carepages.com; his CarePage name is MasterWilliam.

Happy 5th Heart Day, William!
We love you so, so much!


Thursday, June 23, 2011

Parenting a Heart Kid

This is not William's X-ray, but it is an image
of someone with Scimitar Syndrome.
First of all, it turned out to be little more than a fragile, superficial vessel that popped and bled. William’s fine and we, his parents, are thankful to be nothing more than overly tired after a late night in urgent care.

But when your asthmatic, heart kid starts coughing up bright red blood after a coughing episode, you try hard not to work yourself into a panic. That’s what happened last night.

William was minding his own business, taking a shower, and abruptly started coughing. OK. Not unexpected: he has mild/moderate, chronic asthma, and it’s been triggered and exacerbated lately by a lingering respiratory virus, brutally hot weather and intermittent exposure to the smoke from Florida’s wildfires.

When my husband went to check on him, though, he was caught off guard by the bright-red, kind-of-big splotches of blood coming out when William coughed. And it kept coming. Husband went bonkers, scared witless. I tried hard to be just a “regular” parent – ah, he probably just popped a vessel somewhere, or maybe it’s really just a nosebleed traveling down his throat. But I’ll call Capital Health Plan Urgent Care; we’ll see what they want to do.

When I talked to the nurse, I told him my 7-year-old son was taking a shower and started coughing and then there was blood. The nurse didn’t seem overly concerned and asked if my son had been sick.

“He’s had a cough on and off for a few weeks. Dr. Jones saw him a week ago Friday and his lungs sounded a little junky, but when we went to see his pediatric pulmonologist that Monday at Shands, she said he sounded really good,” I told him casually.

I was not going to panic. Just because he’s a heart kid does not mean it’s a big-deal serious thing. I was going to play my “he’s just a regular kid” card, even if I died a little inside doing it.

“Oh. Um, why does your son see a pulmonologist at Shands?,” the nurse inquired.

“He has chronic, but mild asthma, and he has scimitar syndrome. He’s really fine, though. He’s been very healthy this year,” I explained.

“What was the name of the syndrome again?,” the nurse asked?

“Scimitar syndrome. It’s part of his partial anomalous pulmonary venous return, a heart defect,” I said.

“Oh. Has he ever coughed up blood before?,” the nurse asked.

“Years ago when he was a baby and had pneumonia, and then I think it happened once after he had his heart repaired several years ago,” I answered.

“Oh! How far do you live from our clinic?,” he asked.

“About 10 minutes or less,” I answered. “If I have to choose between going to an emergency room or waiting to see our pediatrician in the morning, I will choose to wait and see our pediatrician. I think he’s fine.”

The nurse put me on hold. A minute later, he came back and said, “We’ll wait. Please come now.”

And we did. We saw Dr. Henry Gunter, whom we’ve seen before, and he’s a wonderful, kind and patient physician. He had read William’s chart. He knew William had asthma and he knew he had a “great vein anomaly.”

Dr. Gunter checked William’s ears, eyes, nose and throat. His throat looked red, now raw, but like it had been painted red. Dr. Gunter decided William probably had popped some small vessel in his throat, but just to be sure, he sent William for a chest X-ray.

Aside from the wire that has popped open at the base of William’s sternum, everything looked fine. And even the wire isn’t a big deal. Dr. Gunter was gracious and glad it was nothing more than a popped vessel. So were we!

I give myself credit for appearing to be just a calm, typical parent last night. But I won’t deny that the heart mom’s little voice kept whispering in my ear, “He’s probably fine, but he’s a heart kid with respiratory issues. You can just never really know. The fact is, you might be home in an hour or you might be admitting him to the hospital. You just never know.”

That’s what it’s like. That’s how it feels when you’re the parent of a child with a congenital heart defect, or any other chronic illness. You work hard every day to be just another parent; but there’s always a little piece of you somewhere feeling a twinge of panic when something out-of-the-ordinary occurs.

Because it’s true, you really never know for absolute sure.

Friday, March 18, 2011

My Son is a Teenage Athlete

Martin at one of his lacrosse games. That's my boy!
I’m not an alarmist and I don’t over-dramatize situations, but learning about the sudden cardiac deaths of four teenage athletes has had me a little on edge. My son Martin is a teenage athlete and his brother William has a congenital heart defect (CHD).

Ever since William’s diagnosis of scimitar syndrome on March 10, 2005, the question of whether Martin’s heart is as healthy as it has always seemed has been stuck in the back of my mind. I’ve left it there the past six years because I’m neither alarmist nor paranoid.

Well. Until I followed and read the recent stories about Wes Leonard, 16; Matthew Hammerdorfer, 17; Javaris Brinkley, 16; and hearing a personal story about 17-year-old Sarah Landauer of Gainesville.

I know the debates about young athletes and heart screenings. I know there are no guarantees with anything. Any one of us could be hit by a bus on our way home tonight.

I’ve read the checklist of signs, symptoms and histories for student athletes. That we can check no to most of them does little to assuage my anxiety. But a full-on physical check-up will ease my fears about the risk of sudden cardiac death.  

Martin plays an aggressive, high-intensity sport and he has a brother with a CHD. Martin practices lacrosse with his junior-varsity team 15 hours a week, and he plays one to two games per week, and as the starting right attack, he plays 98 percent of the time in each game. I worry. And it's not unfounded worry.

So, on March 10, 2011, six years to the day of William’s CHD diagnosis, our pediatric nurse gave us the dates for Martin’s EKG and echocardiogram. Martin will have his annual physical plus an EKG on today, March 18, William’s due date. Martin’s echocardiogram is scheduled for March 22, William’s birthday. (I’m really not superstitious, but I hate it when dates and numbers fall freakishly together like that.)

I don’t expect anything but to find out everything is normal with Martin and he gets the whole-hearted all-clear to play sports as much and as intensely as he wants.

But right now, he’s teenage athlete who plays vigorous sports. He has a brother with a congenital heart defect. And within a two-week period recently, four teenage athletes have collapsed playing sports. It’s time for Martin to get that EKG and echocardiogram.

Thursday, December 16, 2010

Not for Me to Reason Why

It was Dec. 16, 2004, and I was driving to work, looking at the impeccably landscaped golf course near my family’s home, watching mist rise from the ponds. As I admired the beautiful morning, I thanked God for it, and for letting me keep my infant son, William.

The day before, we learned that he did not have cystic fibrosis, a degenerative, debilitating disease that would have killed him young, or required a double-lung transplant – neither of which I had envisioned for our dark-haired, big-eyed boy. I was so relieved my older son Martin would have his brother throughout his life, and that my husband and I would not have to bury our child.  


Diane Crim Photography. Used with permission. All rights reserved
 I thanked God again for sparing my family – my own and my siblings’ – the tragedies I had seen befall many of my friends’ families. Terminal illnesses, suicides, tragic accidents. I wondered out loud how all of that worked. How one family experiences typical life events, while another family suffers tragedy, sometimes many heartbreaks. How two people can suffer the same illness, disease, or injury, and one lives while the other dies. 

Four days later, I learned there is no rhyme or reason. On Dec. 20, tragedy befell my family. Jonathan – my sister’s and brother-in-law’s only child, my mother’s grandson, my nephew – died in a single-car crash on Tallahassee’s dark, dangerous Deerlake Road. He was only 16.

I still thank God. But I’ve never again wondered, silently or out loud, how any of this works; there is no sensible or reasonable explanation. I’ve never looked at the world the same way since. I do try even more to live each day with gratitude, reverence and humility.

Monday, November 29, 2010

We Will Miss You, Steve

“Because your whole world can change in 24 hours.” – The Paper (1994)

That’s Steve Catoe’s quote from his latest blog post, “24 Hours at Johns Hopkins.” I know that for Steve’s family, the past 24 hours have changed their whole world.

It is with a very heavy heart that I share with you that Steve died sometime between the late-night hours of Nov. 28 and early morning hours of Nov. 29. He was at his computer, doing what he does best, championing survivors and writing about congenital heart defects (CHD). 

I’d like to think he left us in the wee hours of Nov. 29, the 66th anniversary of the Blalock-Taussig Shunt, which Steve has been writing about over the past two weeks.

“We’re thinking positive thoughts,” his cousin Denise Baldwin told me this morning. “That he’s not in any pain and that he has a whole heart now.”

Just 11 days ago, Steve wrote a post called “Run the Race.” It’s an analogy of his life, living with CHD. He writes about the stumbles and falls he had throughout his life with tricuspid atresia. In true form, Steve talks about fighting the good fight, never giving up and crossing the finish line still standing.

If Steve was tapping away at his keyboard when he passed away, I think he got what he hoped for – he crossed the finish line still standing. Doing what he loved best, doing what he did best. Telling a great story and teaching us what it means to live, no matter what our struggles might be. He made a huge impact on the CHD community, speaking at several events and being there online for more than 400 followers each on Twitter and his blog, Adventures of a Funky Heart, and more than 800 friends on Facebook. He did fight the good fight for so many of us.

Steve was one of the very first people I “met” online when I signed up for Twitter in February 2009. I immediately recognized his CHD (tricuspid atresia), as it is the same heart defect as my friend and Broken Hearts of the Big Bend heart kid, Eliza, had. When Eliza endured her own battles, Steve took time to keep his readers updated on her status and ask for prayers for her. Later, he was a champion for another of our heart kids, McKenzie, who lost her fight to neonatal Marfan syndrome earlier this year.

In February 2010, Steve flew to Tallahassee, Fla., to attend and speak at Broken Hearts’ Regional Forum on Congenital Heart Disease. I got to meet Steve, and also his cousin Denise, who is the one who called me this morning to tell me about Steve’s passing.

At the Forum, Steve — a masterful storyteller with an amazing story to share — talked about his life and his parents and their courage and determination to give their son the very best care they could find.

I feel so fortunate and blessed to have known Steve and to call him my friend. We e-mailed each other often, talking about our blogs, the latest goings-ons in the online CHD community, and life in general. It was through conversations with Steve that I realized that Broken Hearts would be more effective and be of more benefit to those families we could touch in person.

I’ll miss Steve’s advice, his points of view on congenital heart issues, his storytelling, and his quirky sense of humor. He was a part of my everyday life. I already miss him and I wish I’d had a chance to say goodbye. Although knowing Steve, he prefers it this way.

When I got Denise’s call this morning, I was — am still — shocked. I knew Steve had been struggling with the ever-delicate hemodynamic balance that many CHD survivors cope with.

In Steve’s case, he was working with his cardiologist to adjust the diuretic he took for his congestive heart failure. One of the possible side effects of the drug is gout; and Steve recently had been fighting gout. They took him off the diuretic and his gout improved, but he knew his congestive heart failure was worsening because his ankles swelled, he had a constant cough and felt, in general, rundown and tired. 

Denise said, at this point, they believe his heart had been working too hard lately, and it gave out. “But, he has his right ventricle now. His heart is complete,” Denise said, continuing to stay positive (which Steve would surely insist we do).

Although Steve may physically have had only half a heart, spiritually his heart has always been whole. I believe for Steve what I believe for my Dad. Just as my Dad is up there hanging out with all of the ancestors he researched and wrote about, I believe Steve is in Heaven with all the CHD survivors he championed and wrote about, and he’s telling all of them how much we love them and miss them here on Earth.

A few weeks ago, Steve and I were talking (e-mailing) about his upcoming Funky Heart posts. He was planning to crank it up a notch or two. And he did. Just last Friday, Steve wrote one of his most powerful entries about working toward a cure for congenital heart defects.

I know he’s up there talking with his fellow CHD angels, telling them how his readers better keep fighting the fight from sea to shining sea. So, for Steve, let’s keep fighting the fight.


Keeping Steve's family in our hearts and prayers. Arrangements are being made in Bethune, S.C., where Steve lived. I will try to post information when it becomes available. 

Thursday, November 18, 2010

Shadowing My Son's Heart Surgeon

That Friday in the fall, for sure, goes down as one of my most amazing days ever.

I shadowed a doctor who is arguably the best pediatric heart surgeon in the southeast United States, and one of the best in the country. Dr. Mark Bleiweis is the director and principal cardiothoracic surgeon for the UF Health Congenital Heart Center in Gainesville.  

When I asked Dr. Bleiweis over the summer if I could follow him around at work some time, I assumed I would observe him making rounds in the intensive care unit at the UF Health Shands Children’s Hospital in Gainesville. I figured I would sit in on conferences and consultations he had with families whose children were having, would be having, or just had open-heart surgery to repair their congenital heart defects. I guessed that I would sit and watch while he handled administrative work. I was right. I did all those things.

I did not think I would step into his operating room. But I did.

I stood in the very operating room my son had been in four years earlier, about to observe the very surgeon who repaired my child’s heart. At first, it was overwhelming.

For at least an hour, I stood there, kind of numb, thinking: I’m here. I’m in the operating room. I am about to observe open-heart surgery on a baby. I am about to see what my son went through when he was 2 years old, after he left my arms that morning on Thursday, June 29, 2006. 

I took deep breaths and stayed focused on being a writer, taking in as much as I could. I focused on being an advocate, learning more about what happens after we heart parents give our children over to the doctors and nurses who promise to take care of them, repair their hearts, and return them to us whole. I focused on not fainting from the sheer awesomeness of it all.


For more than six hours, I sat, stood, paced, stretched, watched, listened and absorbed everything going on around me while Dr. Bleiweis repaired the swollen, failing heart of a baby.

Born with a complex, life-threatening heart defect called complete atrioventricular canal defect, the baby did not have the typical four chambers and four valves that of a normal heart. She had one large chamber and one valve. 

The baby’s heart defect was so obvious that during the pre-surgery ultrasound of her heart, even my untrained eye could see there were essential chambers and valves missing.

This infant’s heart was working so hard to do its job pumping blood, it was more than twice the size it should have been. Without this surgery, the baby would die.    

I saw Dr. Bleiweis delicately cut away the heart’s protective sac and expose the child’s beating heart. He placed the sac in a solution that makes the flimsy tissue firm and durable; it’s what he would use to make patches to cover the holes in the heart.

The team attached tubes and clamps that led from the baby to the heart-lung bypass machine, which circulates a patient’s blood while the heart is stopped. 

The perfusionist (the person who controls the bypass machine) administered a special mix of drugs called cardioplegic solution to make the baby’s heart slowly stop beating. The perfusionist drained the heart of its blood, and the heart shrank. Throughout the operation, Dr. Bleiweis would ask the perfusionist to fill and drain the heart. It was astounding.

I took turns with medical and nursing students and the anesthesiologist to stand on a stool at the head of the operating table. I gazed over surgical drapes and looked straight down, less than a foot away, into the infant’s open chest as Dr. Bleiweis – using high-magnification lenses – delicately sewed the tiniest stitches into the baby’s imperfect heart.

On this day, Dr. Bleiweis was clearly the leader in the operating room. His requests, directives and commands were clear, direct, exact and instructive. His team might not have always liked what they heard, particularly if he was correcting them, but his criticism was constructive and designed to make his team that much better during the very next operation and every operation after that.

During the four-plus-hour operation, Dr. Bleiweis meticulously patched the holes between the baby’s upper chambers (the atria) and the lower chambers (the ventricles), forming a wall between left-side and right-side chambers. He created two functioning valves – a tricuspid valve and a mitral valve.

His work was so exacting, so intricate and so complete that as I watched the post-surgery ultrasound of the heart, I could clearly see the wall in the center of the heart and the two valves that Dr. Bleiweis created for the baby. The baby’s heart would never be normal, but now it would work as efficiently as it ever could. It was extraordinary.

The science and precision weren’t the only remarkable, memorable aspects of watching this elite team of surgeon, nurses, anesthesiologists and perfusionists.


Dr. Bleiweis, who can operate on the grape-size heart of a newborn baby who’s no bigger than a water bottle, could easily be arrogant or condescending. And yet, he is consistently professional and gracious – to his team, his staff and, especially, to his heart families. I’m still absorbing everything I saw that day, but here are thoughts that have stuck with me:
  • I am amazed and struck that a pediatric heart surgeon must map out – sometimes in a matter of days and other times in a matter of minutes – the best surgical option for a child whose heart is complicatedly misconstructed.
  • There is no room for mediocrity in pediatric heart care – not in preoperative procedures, during an operation, or in postoperative care. Pediatric heart teams persistently reach for excellence. Every single day.  
  • In the operating room, everyone must work cohesively. They must anticipate what the person next to them will need next, do next, ask for next. They must foresee what their patient will do next, will need next. And they must be there, ready. If there are personality conflicts, hard feelings, or bad attitudes, they’re not perceptible. Everyone in the room works harmoniously, willingly, gladly and always with one goal in mind – the care and comfort of the patient.  
  • Dr. Bleiweis and his team sweat not just the small stuff, but the minutiae, every hour of every day. And I – along with hundreds of other heart families each year – am very grateful that they do.  
  • I’m inspired that parents can and do entrust their child’s life to the hands of a surgeon – most often, a person they’ve met only briefly – who promises to repair their child’s misassembled heart. I am even more moved that there are people willing to accept that mammoth responsibility as humbly as Dr. Bleiweis and his team do.  
  • I am utterly, wholly and completely awed that this is what this team does: they fix babies’ hearts. They save babies’ lives. Every. day.

          Saturday, November 13, 2010

          William Scores His First, Long-Awaited Soccer Trophy

          Since William was 3, he has begged for his brother to give him one of
          his dozen, prized soccer trophies. We, of course, have told William
          when he plays soccer when he's older, he'll earn his own soccer trophy.
          He just had to be patient. Today was the day he earned his first trophy!
          Dear Coaches Stephen and Brian:

          Thank you so much for being great coaches. It’s been such a positive start to William’s soccer “career.” Not every volunteer coach gets the right mix of skill-building, fun and positive reinforcement, but you both got it right all season.

          So you know just what a wonderful milestone this soccer season has been for our family …

          Letting William run free and wild on the field, and letting him decide when he needs to take a break, has been a huge step for us. William was born with a heart defect. When he was 2 years old, his heart was repaired through open-heart surgery at Shands Children's Hospital.

          William has always had the all-clear to play whatever sports he likes, but as worried parents who weren't sure what a "heart kid" could do, we bite our nails – and have had to learn to bite our tongues – when William plays sports. We have to remind ourselves that he really is just a regular kid.

          Watching William in his first practice and in his first game were sweet, sweet milestones. Because there were times, when William was a baby, that we weren’t sure he would make it at all, never mind be able to run around on a soccer field, passing the ball to his teammates and scoring goals. I've never seen a kid smile so much running up and down a soccer field. William has had a blast, and Joaquin, Martin and I have totally enjoyed watching him play.

          Thank you both for helping make William’s first soccer season such a memorable one. We are very grateful.

          Karen, Joaquin and Martin

          Tuesday, June 29, 2010

          Always Grateful

          My now 6-year-old son William spent most of the first year of his life sick. Constantly sick. No one seemed to be able to figure out what was wrong. One doctor kept telling us William was sick because he was in daycare.

          Finally, just 12 days short of his 1st birthday, William was diagnosed with scimitar syndrome (sometimes called partial anomalous pulmonary venous return). A year after that -- four years ago today -- on June 29, 2006, William's beautiful little heart was repaired at Shands Children's Hospital at the University of Florida.

          We are ever, ever grateful to Dr. Mark Bleiweis for his special gift of fixing babies' hearts. We thank God often, still today, for pediatrician Dean Dalrymple and pediatric radiologist Charles Williams for their sense of urgency, curiosity and diligence in getting to the root of William's illnesses. If not for these amazing people, we might still be wondering what was wrong. And we are always thankful for William's pediatric cardiologist, Dr. Jay Fricker, who makes sure William continues to do well. 

          One of William's biggest supporters and cheerleaders, though, doesn't often get public praise, but he certainly deserves it for his eternal patience, his constant support, his everyday care and never-ending hugs and love. I think God specifically chose Martin as William's big brother because He knew that William would have a rough start in life and that Martin would take extra-special care of William. They have a beautiful brotherly bond, especially for siblings who are nine years apart. They are best Bubbas.

          After four years, 14 years, 40 years, we will always pause on this day -- June 29 -- and thank God for His presence in William's and our lives, and for guiding us to the people William needed to be whole and healthy.

          Happy Heart Day, William. We love you and are so glad you are here and whole and healthy and happy.

          Sunday, May 9, 2010

          When Doctors Fail

          Adventures of a Funky Heart writer Steve Catoe posted a story I sent him over the weekend about a heart mom I know who lost her baby at 40 days old.

          Michael should still be here. He would be 2, and this Sunday would have been his third Mother's Day.

          One mom who read this post asked if there was anything she could do. There is: Tell every heart parent you meet and know to be sure their child is seen and evaluated by board-certified pediatric heart specialist. Trust your instincts. Ask questions. Expect answers. Don't tolerate ego. Demand to be part of your child's care and treatment. Advocate, advocate, advocate.

          Thursday, April 8, 2010

          Medical-Specialty Board Certification: It Matters

          “Any doctor can deliver a baby, treat cancer, or declare himself a cardiologist. Certification means the doctor had special training in that field and passed an exam to prove knowledge of it.”

          Six years ago, I would have said Associated Press writer Marilynn Marchione was exaggerating in her recent article, Doctors face board specialty 'expiration dates'.

          Had my son never landed in the hands of a physician who “declared” himself a specialist, I might still think that way. But he did. So I don’t.

          In a previous post about my son William’s heart murmur, I mentioned “the eight-month-long road to a correct diagnosis was ill-paved and rife with potholes.”

          I’d like to explain now.

          At William’s four-month well-baby checkup, his exam revealed The Heart Murmur. The pediatrician (whom we no longer see) referred my son to a specialist -– “a pediatric cardiologist,” the pediatrician said -– to evaluate the murmur.

          If only I’d known then, what I know now: verify credentials yourself. You can’t rely on referring physicians. They might not have verified credentials. They might be assuming a specialist is certified. Or, the specialist might be so rooted in the community that everyone assumes he/she is a board-certified specialist.

          You also can’t rely on advertising -- even though (in Florida anyway) claiming you’re board certified in an area you are not board certified in is against the law.

          If I could do it again, my first stop would have been here, so that my second stop could have been with a real pediatric cardiologist. Despite what the pediatrician said, the local physician who sees pediatric heart patients is not this area’s “only option.”

          Knowing what I know now, I'm not at all surprised this physician misdiagnosed my son. Not just once, but twice. This doctor is nothing more than a pediatrician who completed a pediatric cardiology fellowship ... 35 years ago. Since he's not board certified in pediatric cardiology, there's nothing to show he has pursued any continuing medical education (CME) in this area.

          And there have been so many advances in CHD diagnosis, research and treatment over the past three-and-half decades, it hardly seems possible he could have stayed relevant without a lot of CME.

          Physicians I love and trust implicitly have told me William’s congenital heart defect (Scimitar Syndrome) is not an easy one to diagnose -- implying I should cut the doctor some slack.

          But if it's so hard to figure out, I ask them, then please explain how William’s eventual correct diagnosis was made by a mere pediatrician and pediatric radiologist? Neither of them specialize in, or have had concentrated study in pediatric cardiology.

          Really, if not a pediatric cardiologist, then who is imminently qualified to diagnose congenital heart defects -- even those that are difficult to diagnose? If you're going to "declare" yourself a pediatric cardiologist, then you'd better well know what you're doing!

          After William's diagnosis, we requested a referral to the University of Florida Congenital Heart Center -- one of this area's many options. The physicians there are extremely competent, very compassionate and ... board certified.

          About 15 months after William's open-heart surgery, I filed a formal complaint with the Florida Department of Health. The complaint included misdiagnosis of condition and false advertising. However, DOH declared the physician had done nothing wrong. Nothing. Not even falsely advertising himself.

          I also e-mailed the American Board of Pediatrics about the physician’s advertisements. Although the ABP can’t tell me what, if any, action it took, I noticed that about six weeks later, the physician no longer held himself out in advertisements as a board-certified pediatric cardiologist.

          Marchione writes in her article, “The next time you’re at the doctor’s office, take a peek at those certificates hanging on the wall. Like gallons of milk, some of them are expiring.”

          Better yet, make sure from the start they even have certificates.

          The American Board of Pediatrics sponsors a campaign called “Certification Matters.”

          And let me tell you: It. So. Does.

          Wednesday, March 3, 2010

          Scimitar Syndrome: A Discovery Highlight

          If you’d told me in high school that one day, I would read abstracts from the Annals of Thoracic Surgery with the giddy delight of a 5-year-old eating an ice-cream sundae, I would have burst out laughing, and, well, I would not have believed you for even a second.

          But here I am (more than two decades later), all excited over an abstract I found online from a 2009 edition of the Annals of Thoracic Surgery. The article is about a multicenter study in Italy of patients with scimitar syndrome.

          Scimitar syndrome is a rare variation of partial anomalous pulmonary venous return, a congenital heart defect. And my almost-6-year-old son is one of the 1-3 in 100,000 babies who are born with scimitar syndrome, and one of the 1 in 125 babies born each year in the United States with a congenital heart defect.

          I’ve learned a lot about scimitar syndrome since those first months after William’s diagnosis in March 2005. And finding the abstract today was a highlight of my discoveries.

          The study included 26 patients. Most of the patients presented like my son, with symptoms including recurrent upper respiratory tract infections and pneumonia. Eighteen of the patients had an intraatrial baffle repair, while eight patients had their scimitar veins moved and re-implanted at the left atrium.

          Those were the two repair options William’s brilliant pediatric heart surgeon — Mark Bleiweis at the University of Florida Congenital Heart Center — discussed with us. He said he wouldn’t make a decision about which repair to use until he saw William’s heart. Then he would figure out which would be the better solution.

          Once inside William’s chest, Dr. Bleiweis thought William’s left atrium was a bit small to accommodate the right pulmonary veins, so he created an intraatrial baffle — a tunnel directing the blood flow from William’s anomalous right pulmonary veins (located near the junction of the inferior vena cava and the right atrium) into his left atrium, where it belonged.

          We knew then that Dr. Bleiweis knew what he was doing, and we trusted him. Now I’ve found a study of 26 patients over a 10-year period that shows “the intraatrial baffle repair seems to have a lower incidence of postoperative complications and a better patency rate, at last follow-up, than the re-implantation of the scimitar vein onto the left atrium.”

          We’ll take it.

          Thursday, January 28, 2010

          The Heart Murmur

          I did it when my 14-year-old son was a baby. And I was doing it now. Holding my breath. Praying. Watching the pediatrician’s face. He was listening to my 4-month-old son’s heart and lungs during a routine well-baby check-up.

          One minute. Two minutes. My son’s chest. His back. Three minutes. Four minutes. His chest. His back again. This is taking too long. He is listening to my baby’s heart too long. I closed my eyes and prayed.

          The doctor rolled back his chair to look at me. I looked at him, thinking, praying ... Don’t say it. Please don’t say it.

          “I hear a murmur.” He said it.

          I pulled my son, William, tighter to my chest.

          “Most of the time, these things turn out to be nothing, Ms. Chavez,” the pediatrician gently told me. “But this sounds significant; I’m afraid this is going to turn out to be something.”

          “I’m going to refer you to a pediatric cardiologist,” the doctor explained.

          My own heart dropped. There was a problem with my baby’s heart. His heart.

          I wanted to rewind that day. July 30, 2004. It had been just a normal day. Now it was anything but.

          “If this is something,” I asked the nurse practitioner on my way out, “what do I look out for? How will I know if something has happened or has gone wrong?”

          “He’ll have trouble breathing, he’ll look blue,” she answered in a hurry as she went to see another patient. But she looked sad.

          That was it? That wasn’t nearly enough information. I was terrified. I cried all the way home from the doctor’s office. I reached toward the backseat, trying to hold William’s hand. I realized I had to tell my husband our infant son has a heart murmur and needs to see a pediatric cardiologist.

          The innocence and naïve joy of having a new baby were gone. Everything changed that day. Our lives were never going to be the same.

          Unfortunately, the "pediatric cardiologist" we were referred to in Tallahassee was not board certified. The eight-month-long road to a correct diagnosis was rife with potholes and detours. We spent five months in the hands of physicians who were poor listeners and even worse diagnosticians. The local "pediatric cardiologist" twice failed to correctly diagnose William's heart defect. 

          It was a fearful, heartbreaking, stressful time. William was never well. I developed Bell’s palsy that September and my 16-year-old nephew was killed in a car crash five days before Christmas.

          After that, getting William well took on new meaning and our efforts to do it amplified. We “fired”’ our pediatricians and found a new one. One who listened, examined and treated carefully, methodically and cautiously.

          William’s correct diagnosis – scimitar syndrome, a rare variation of partial anomalous pulmonary venous return – came just days before his first birthday. (William's version of scimitar syndrome includes an underdeveloped right lung that receives no blood flow; he functions entirely on his left lung. He also right pulmonary vein stenosis, mild right ventricular hypertrophy and superior vena cava stenosis.) The diagnosis was the result of the divine meeting of the medical minds of two thorough and thoughtful physicians. 

          The first thorough and thoughtful physician was our new pediatrician who had immediately questioned and investigated the diagnosis that William’s heart murmur was functional. He thought it sounded pulmonary and was concerned because he could hear the murmur in William’s back. Functional murmurs, he said, typically can only be heard through the chest.

          The second brilliant mind was a pediatric radiologist who had read two sets of William’s chest X-rays – four months apart – and noticed the same problem in each: William’s lungs were unequal in size and function. Of all the patients that pediatric radiologist sees in the hospital and in his radiology practice – and he remembers my son and these minute details of his lungs. That still amazes me.

          Once William was diagnosed, we were referred to the UF Health Congenital Heart Center in Gainesville. That's when everything started to get better. We learned so much about William's particular condition and we no longer feared that he would drop dead while he was running in the yard with his brother. And wonderfully, at UF Health, we continued to find doctors who listened, examined and treated carefully, methodically and cautiously.

          I hug, kiss and tell my children every day that I love them. I stare at them and marvel at their beings, their health and their lives. I will never forget William’s four-month, well-baby check up and hearing those words “heart murmur.”

          Those words and all the days that have followed have changed our lives forever. I would not have believed it then, but I know now, they have changed for the better. Our family is a stronger family. We appreciate our lives in ways we never did before. We have an incredible team of physicians for William's continued care. We have met hundreds of families online and in real life who have similar experiences as ours. We have William's heart to thank. We didn't think it then, but we know now, we wouldn’t have William’s heart any other way.


          Updated: Feb. 3, 2018.

          Pages